
PCT / HCG / HMG - Post Cycle Therapy
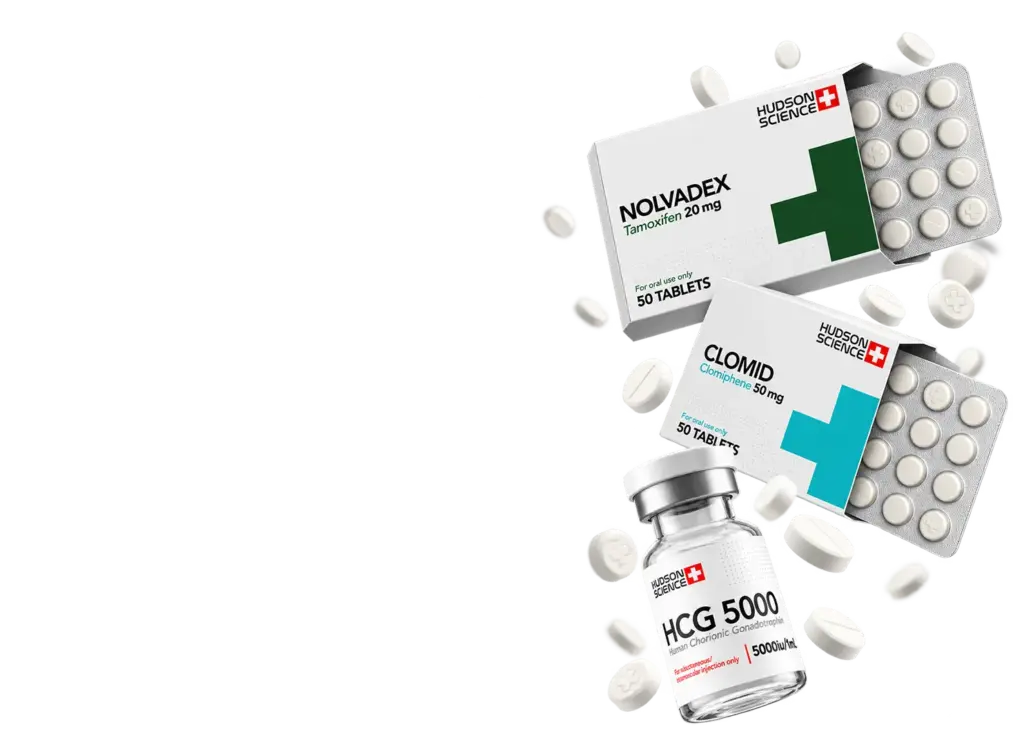
Nolvadex, Clomid, HCG, HMG and everything you need to recover your natural hormonal function after a suppressive cycle. Every PCT compound independently lab tested by Janoshik or Testides, sourced from verified manufacturers, shipped discreetly across Canada.
Independent Lab Testing
Every PCT compound is third party tested by Janoshik or Testides before listing. An underdosed SERM or HCG doesn't just underperform; it leaves your hormonal axis suppressed for longer than it needs to be.
Verified Manufacturers
Hudson Science, Porta Biologico and other vetted brands. PCT compounds are too important to source from unverified manufacturers, every brand on our site is confirmed before listing.
Complete PCT Toolkit
SERMs for LH and FSH stimulation, HCG for testicular function, HMG for FSH support and spermatogenesis; every compound needed to build a complete, properly structured PCT protocol.
Discreet Canadian Shipping
Plain, unmarked packaging with no indication of contents. Fully tracked, delivered anywhere in Canada within 3–5 business days.
PCT / HCG / HMG - Post Cycle Therapy

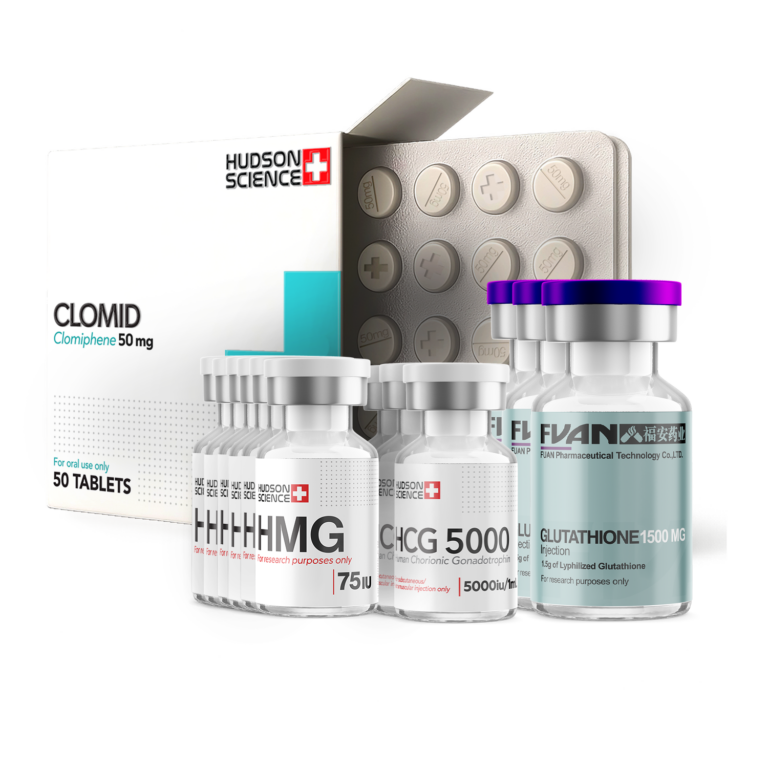


HCG 25000IU - 5 VIALS of 5000IU [Testosterone production] - ( Certificate of analysis, second image )

HMG 75IU [Fertility + LH boost]







Glutathione 1500mg [Cellular detox]




Overview
Post Cycle Therapy in Canada | Nolvadex, Clomid, HCG & HMG
Post cycle therapy is not optional. Every suppressive compound, anabolic steroids, SARMs, prohormones shuts down the hypothalamic pituitary gonadal axis to some degree. Your body stops producing its own testosterone because exogenous androgens have made the signal from your pituitary redundant. When the cycle ends and those androgens clear, the axis doesn’t automatically restart on its own timeline it needs to be actively stimulated back into function. That’s what PCT is for.
A poorly planned PCT or no PCT at all means weeks to months of low testosterone, elevated estrogen relative to androgens, loss of cycle gains, suppressed libido, mood disruption, and potential long term impact on natural hormonal function. A well executed PCT using the right compounds at the right doses shortens that window dramatically and protects everything you built during your cycle.
True North Performance carries the complete PCT toolkit: Nolvadex, Clomid, HCG, and HMG, every compound independently tested by Janoshik or Testides before listing. PCT is exactly the wrong category to cut corners on sourcing.
Nolvadex (Tamoxifen Citrate) Canada
Nolvadex is the most widely used SERM for post cycle therapy. The compound most athletes reach for first and the benchmark against which every other PCT option is measured. It works by blocking estrogen receptors at the pituitary level, which removes the negative feedback signal suppressing LH and FSH production. The result is a rapid increase in gonadotropin output, which stimulates the testes to resume natural testosterone production.
Standard Nolvadex PCT protocol: 40mg per day for two weeks, followed by 20mg per day for two further weeks. For standard cycles, testosterone based, 12–16 weeks, this four week protocol is sufficient for most users. For longer or more suppressive cycles, Nolvadex is commonly combined with Clomid for a more aggressive recovery.
Clomid (Clomiphene Citrate) Canada
Clomid is the second primary SERM used in PCT. Like Nolvadex, it blocks estrogen receptors at the pituitary to stimulate LH and FSH release but it has a stronger FSH stimulus than Nolvadex, making it particularly useful in protocols where spermatogenesis recovery is a concern alongside testosterone restoration. Clomid also has some direct testicular effects that complement the pituitary stimulus.
The two compounds are often combined in more aggressive PCT protocols, Nolvadex handling the primary LH stimulus with Clomid adding FSH support. Standard Clomid PCT doses run 50mg per day for the first two weeks, dropping to 25mg per day for weeks three and four. Side effects could be visual disturbances and mood disruption but are dose dependent and more common with Clomid than Nolvadex, which is why Nolvadex is typically the first choice for standard cycles and Clomid is added when extra recovery support is needed.
HCG | The PCT Bridge
HCG mimics LH at the testicular level, directly stimulating testosterone production and maintaining testicular size and function during suppressive cycles. The most important thing to understand about HCG in PCT is the timing; HCG is most effective when run during the cycle or as a bridge immediately before starting SERM based PCT, not simultaneously with SERMs.
Running HCG during the cycle with about 250–500 IU twice weekly keeps the testes active and responsive throughout suppression, so that when PCT begins, they’re primed to respond to the LH and FSH stimulus from your SERM rather than starting from a dormant baseline. For longer or more suppressive cycles anything involving Nandrolone Decanoate, long ester testosterone at high doses, or extended durations incorporating HCG on cycle is strongly recommended.
For users who didn’t run HCG during their cycle, a two week HCG bridge at 500–1000 IU every other day after the cycle ends and before SERM PCT begins restores testicular responsiveness and makes subsequent SERM based recovery significantly more effective.
HMG | FSH Support for Comprehensive Recovery
HMG (Human Menopausal Gonadotropin) contains both LH and FSH activity, making it more comprehensive than HCG alone for protocols where spermatogenesis recovery is a specific priority. While Clomid stimulates FSH release indirectly via the pituitary, HMG provides direct FSH stimulus, the same approach used in clinical fertility medicine for cases of significant gonadotropin deficiency.
In practice, HMG is used in conjunction with HCG for more aggressive recovery protocols typically in users who have run multiple long cycles, have documented suppression on bloodwork, or have fertility concerns that standard SERM based PCT hasn’t adequately addressed.
Building Your PCT Protocol
The right PCT depends on what you ran and for how long. A standard 12 week testosterone only cycle needs a straightforward four week Nolvadex protocol. A longer cycle involving Nandrolone Decanoate, which has a significantly longer half-life and clears slowly needs a longer wait before PCT starts, HCG during or bridging the cycle, and potentially Clomid combined with Nolvadex for the SERM phase. A cycle involving multiple suppressive compounds over extended periods may warrant adding HMG alongside HCG and a full combined SERM protocol.
Bloodwork before, during, and after your cycle is the most reliable way to know where you stand and whether your PCT worked. Total testosterone, free testosterone, LH, FSH, and estradiol at minimum, ideally with a full blood panel to monitor overall health markers throughout.
Explore
Shop PCT by Compound
Steroids | What You're Recovering From
The suppression profile of your cycle determines how aggressively you need to recover. Browse our full steroid catalogue: injectables, orals, and testosterone compounds to plan your PCT around what you ran.
Shop Steroids (opens in a new tab)HCG & HMG | Fertility & Testicular Function
HCG for on cycle testicular maintenance and PCT bridging. HMG adds the FSH stimulus needed for comprehensive spermatogenesis recovery. Browse our fertility compounds for the full gonadotropin support range.
Shop HGH (opens in a new tab)Estrogen Management During Recovery
Estrogen doesn't manage itself during PCT. If AI support is needed alongside your SERM, Aromasin is the correct choice, it doesn't interact with Nolvadex the way Arimidex does.
Shop Estrogen & Prolactin Control (opens in a new tab)Estrogen & Prolactin Control
Managing estrogen during and after your cycle is part of complete hormonal recovery. Browse our Estrogen & Prolactin category for aromatase inhibitors and dopamine agonists.
Shop Estrogen & Prolactin Control (opens in a new tab)Education
PCT Guides & Resources

Best PCT Cycles: 100% Testosterone Recovery in 4-6 weeks
_________________________________________________ TLDR: Skip to the bottom to check out the synopsis of this article with the key takeaways to help you better understand why post-cycle therapy is so…
Purchase HGH in Canada: Top Quality Options & Fast Shipping
Have you been searching the web trying to figure out where you can buy HGH in Canada? This guide will help you navigate the necessary considerations and various…
Support
Common Questions About Post Cycle Therapy in Canada
When should I start PCT after my cycle?
Timing depends on the esters you ran. For long ester compounds like Testosterone Enanthate or Cypionate, wait two weeks after your last injection before starting your SERM as this allows the ester to clear and testosterone levels to drop enough for PCT to be effective. For short esters like Testosterone Propionate, wait three to four days. For Nandrolone Decanoate (Deca), wait three weeks due to its significantly longer half-life. If you ran HCG as a bridge post cycle, begin your SERM immediately after the HCG phase ends.
What is the standard Nolvadex PCT protocol?
The most widely used Nolvadex PCT runs 40mg per day for two weeks followed by 20mg per day for two weeks, four weeks total. For more suppressive cycles, this is often combined with Clomid at 50mg per day for weeks one and two, dropping to 25mg per day for weeks three and four. Always start PCT at the right time based on your ester clearance, starting too early wastes your SERM while androgens are still suppressing the axis.
Do I need both Nolvadex and Clomid for PCT?
For standard cycles a single testosterone ester at moderate doses for 12–16 weeks Nolvadex alone is sufficient for most users. Combining both is recommended for longer cycles, higher doses, cycles involving multiple suppressive compounds, or any cycle that included Nandrolone or Trenbolone. If fertility recovery is a specific concern, adding Clomid for its stronger FSH stimulus is worthwhile regardless of cycle length.
Should I run HCG during my cycle or only for PCT?
Ideally both, for cycles of any significant length. Running 250–500 IU of HCG twice weekly throughout a suppressive cycle maintains testicular function and prevents atrophy, making PCT significantly more effective when the time comes. If you didn’t run HCG during your cycle, a two week bridge of 500–1000 IU every other day after your last injection, before starting SERM PCT which will restores testicular responsiveness and improves PCT outcomes.
Can I use an aromatase inhibitor during PCT?
Generally not recommended as a primary strategy. The goal of PCT is to restore hormonal function, some estrogen is needed for LH and FSH sensitivity and for overall wellbeing during recovery but crashing estrogen during PCT extends recovery time and worsens the low testosterone symptom window. If your estrogen is confirmed elevated on bloodwork during PCT, Aromasin is the correct AI to use alongside Nolvadex, Arimidex interacts with Nolvadex pharmacokinetically and reduces its effectiveness.
How do I know if my PCT worked?
Bloodwork is the only reliable answer. Get total testosterone, free testosterone, LH, FSH, and estradiol tested four to six weeks after completing PCT. Recovery targets vary by individual but you’re looking for testosterone back in normal physiological range, LH and FSH active and present, and estradiol in appropriate ratio. If levels haven’t recovered adequately, an extended PCT or consultation with a healthcare provider is the appropriate next step.
Do SARMs require PCT?
Suppressive SARMs like LGD-4033, RAD-140, YK-11 cause meaningful testosterone suppression and benefit from a SERM based PCT. A standard four week Nolvadex protocol at 20mg per day is generally sufficient after a single SARM cycle at standard doses. Milder SARMs like Ostarine at low doses for shorter cycles cause less suppression, though bloodwork post cycle is the only way to confirm whether PCT is needed for a specific individual.